What makes tingling a different question?
A locally painful attachment and a tingling finger are different phenomena. They can exist together, but do not automatically ask for the same treatment. Therefore, tell emotional changes separately, even if you've gotten all the label tennis arm or golf arm.
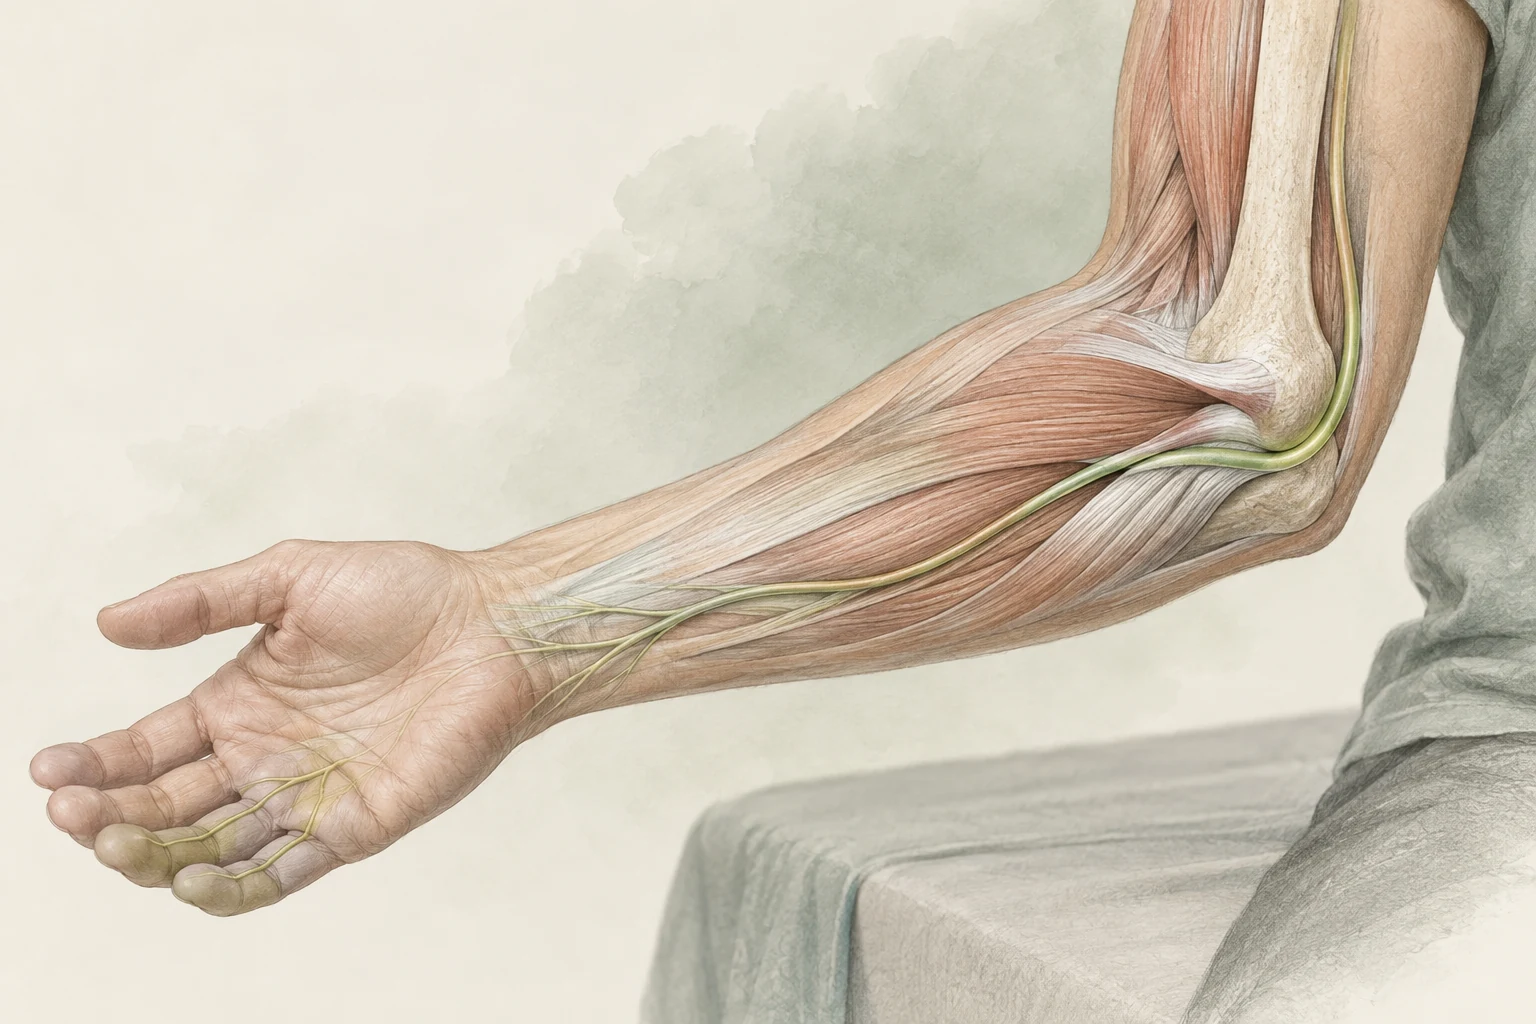
Radboudumc describes that a malfunction of the ulnar nerve can cause tingling or numbness in pinky and ring finger. Handpower and skill can also be reduced.
This pattern is a clue to investigation, not self-diagnosis. Other causes are possible and a doctor looks at the whole. So you don't have to prove to yourself that a nerve is trapped. A clear description of location, gradient and function is sufficient to get the right question on the table.
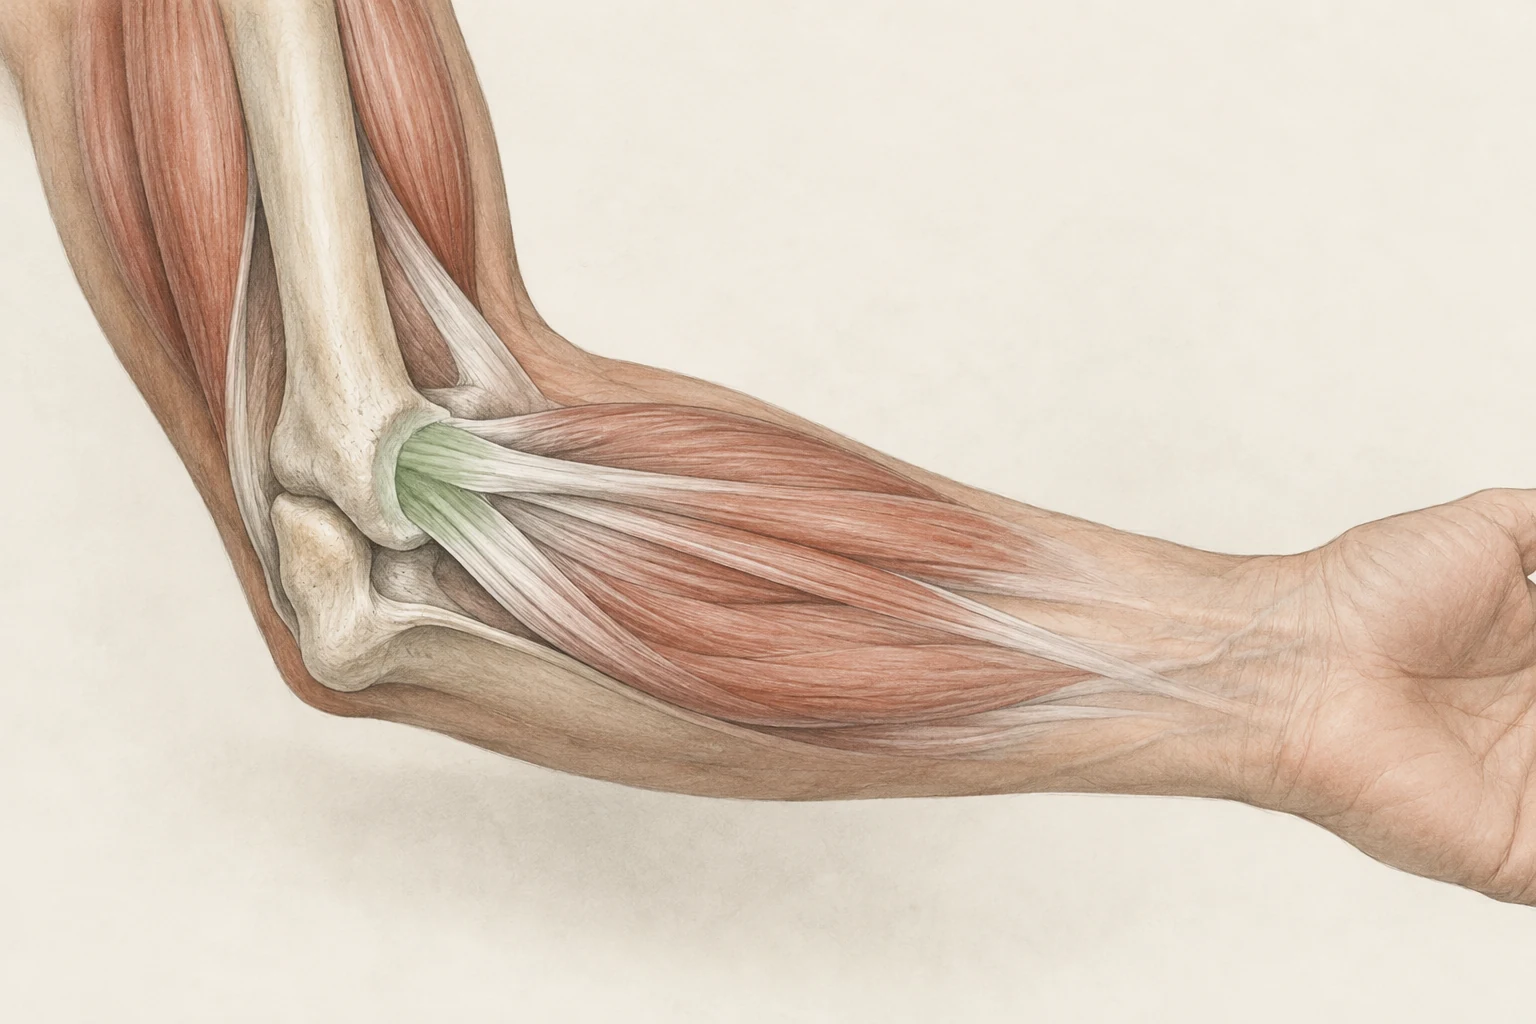
The nerve runs along the inside of the elbow
The ulnar nerve runs through the inside of the elbow to the hand. The electrical feeling of bumping the phone bone gives many people a recognizable picture of that area. Sustained symptoms, however, are something other than a short bump.
Pressure on the elbow or prolonged strong bending may be relevant with a pinched or irritated nerve. The Diakonessenhuis mention examples such as support during computer work, driving or a curved arm during sleep.
Don't go beating the area all the time to stir up the tingling. That does not provide a reliable diagnosis and can be especially annoying. Prefer to record the usual situation in which the symptoms occur and what attitude you had at the time.
Describe feeling and strength separately
Try to keep three parts apart: pain, altered feeling and difficulty with an action. Write, for example, tingling in two fingers after long bending or grasping small objects is less accurate. That's more useful than all the symptoms together call poor weakness.
Mind the course, too. Are the tinglings short-lived or does the feeling remain different? Did something new come into being? Do you notice objects falling out of your hand more often? Report such changes to the review.
A lower pain score is not always enough reason to wait when feeling or strength deteriorates simultaneously. The hospital information describes that ulnar neuropathy may range from mild symptoms to apparent change of function. Therefore, the whole manual function should be included.
What happens when research is done?
The assessment begins with your story and physical examination. A doctor looks at strength, feeling and hand function. In case of unclearness or to further assess the diagnosis nerve conduction research and ultrasound can be used. What studies are needed varies from one situation to another.
Ask what every investigation needs to answer. A nerve ultrasound and an ultrasound aimed at a painful tendon are not automatically the same question. A finding on an image should also fit in the symptom pattern.
Bring previous research reports if you've already been treated. Specify treatments on or around the elbow and medication. You do not have to draw a medical conclusion; the aim is that the assessor has a full time span and knows what is already known.
Gathering practical information without treating yourself
A short observation list can support the consultation.
| Subject matter | What can you write down? |
|---|---|
| Location | Which fingers or which part of the hand? |
| Situation | Sleeping, calling, driving or desk work? |
| Attitude | A lot of bending or leaning directly on the elbow? |
| Duration | Short-term or lasting change of feeling? |
| Function | Trouble with grabs, buttons or small objects? |
Reduce pressure where possible that clearly provokes symptoms, but do not create a tight homemade splint. Specific tools or nocturnal positioning are discussed with your clinician. They may assess whether the purpose and implementation are appropriate.
Example: you notice tingling during long phone calls with strongly curved arm. That is useful information for an opinion on attitudes. It still doesn't prove exactly where a possible nerve constriction is.
When do you want to talk faster?
Get in touch in time for increasing hand weakness, permanent loss of feeling or decreasing fine hand skills. In case of severe or progressive symptoms, treatment weighting may be different from mild, varying symptoms. The Diakonessenhuis describes that severity and loss of strength are part of the choice between adjustments and possible further treatment.
After a new accident or a sudden dropout, you should not first experiment with tools. Request medical assessment of the change.
Shockwave for a supposed tendon symptom is not an answer to unexplained tingling. The most important thing is to identify which structure and function require attention. An existing treatment pathway should be able to be re-examined when new information gives rise to this.
Frequently asked questions
Do tingling in pinky and ring finger always mean ulnar neuropathy?
No. It is a recognizable pattern that may give rise to the examination of the ulnar nerve, but not self-diagnosis. A doctor also assesses other possible explanations. Tell me where the feeling changes, when it happens, and if your hand function is different.
Could a nerve problem exist next to a tendon symptom?
It's possible. Therefore, pain, feeling and strength should be discussed separately. The fact that a tendon insertion is sensitive does not automatically explain tingling or permanent hand weakness. A complete assessment will prevent all phenomena from being attributed to one label.
Do I need surgery right away?
Not automatically. The hospital information describes adjustments and guidance for mild to moderate symptoms, with further treatment depending on course and severity. Increasing power loss deserves timely consultation. Only on the basis of a blog that consideration cannot be made.
Is an ordinary elbow brace suitable?
Don't just buy a tire for tennis elbow if you have tingling. The purpose and place of pressure can be different from a nerve problem. Discuss any tools with the clinician, especially when you notice less feeling, weakness or skin problems.
Sources and evidence
- Radboudumc: Ulnar neuropathy at the elbow ↗
Anatomy, emotional changes, hand function and targeted nerve diagnostics.
- Diakonessenhuis: Curved elbow nerve (2026) ↗
Relationship with pressure/bending, individual approach and importance of increasing power loss.
A personal follow-up step
From insight
to an appropriate plan.
At a paid intake, we'll discuss your symptom and do targeted research. ultrasound is included at no extra cost when it makes sense. Any treatments are agreed separately.
View the initial consultation